
🇰🇼 MOH Kuwait
Specialist General Surgery Kuwait
Physicians preparing for the General Surgery exams of DHA, DOH, MOHAP, Qatar DHP and SCFHS
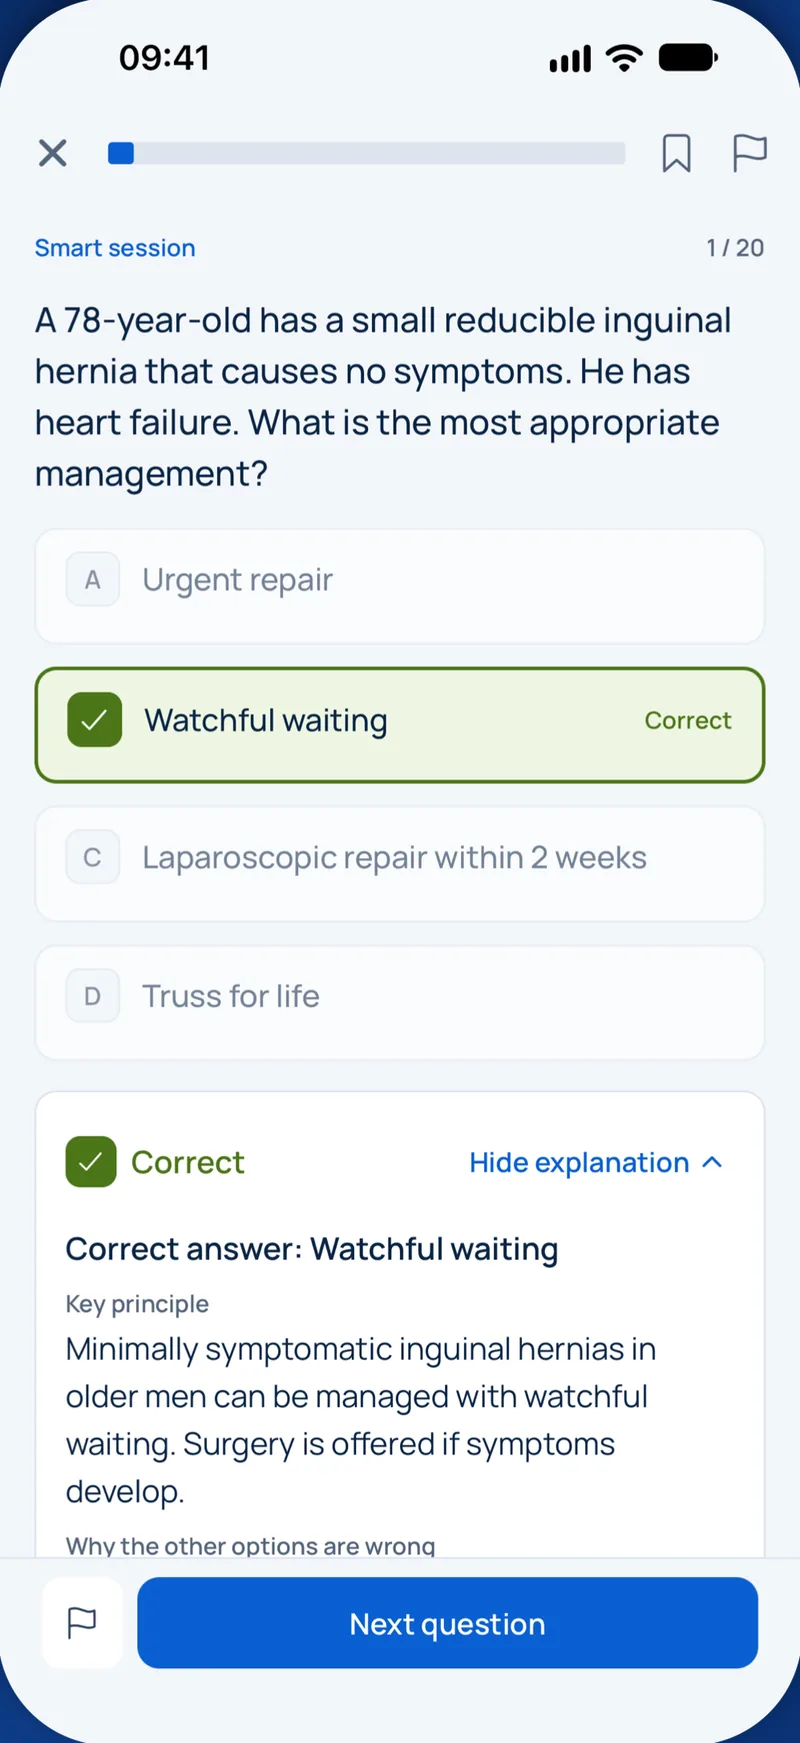
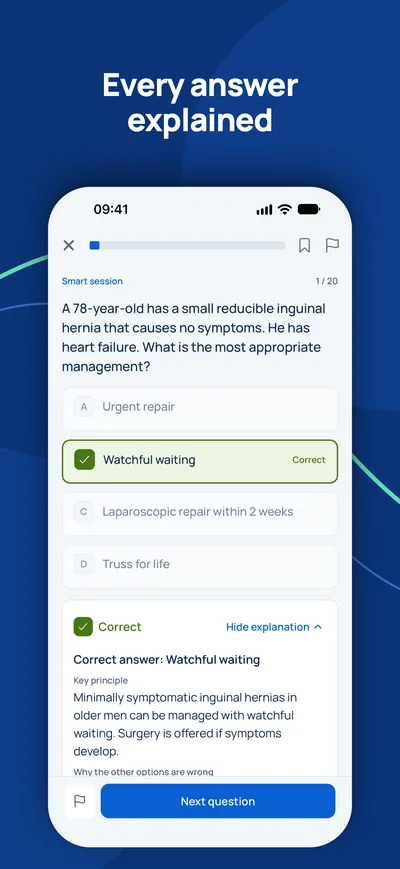
Domanda di esempio
A 60-year-old man has an elective hemicolectomy under an enhanced recovery pathway. Which component is part of standard ERAS care?
Keys: 1–5 or A–E to choose, Enter to check and continue, F to mark.
Original MediFlow content, not official exam questions. Medical review in progress.
Syllabus and high-yield notes
1. Perioperative care, fluids & nutrition · 10 % peso nell’esame · 0 lessons+
- Enhanced recovery pathways combine carbohydrate loading, limited fasting (solids to 6 hours, clear fluids to 2 hours), opioid-sparing multimodal analgesia, early feeding and early mobilisation, and shorten stay without raising complications.
- Perioperative cardiac risk is stratified first by urgency, then by functional capacity (METs) and surgical risk. Further testing is only worthwhile if it changes management; routine coronary revascularisation purely to get a patient through non-cardiac surgery does not improve outcome.
- Severely malnourished patients (weight loss over 10 to 15 per cent in 6 months, BMI under 18.5 kg/m2, albumin is a poor marker) benefit from 7 to 14 days of nutrition support before major GI surgery, preferably enteral. Refeeding syndrome is prevented by thiamine and slow caloric build-up.
- Antibiotic prophylaxis is given within 60 minutes before incision (120 minutes for vancomycin or fluoroquinolones), repeated after two half-lives or major blood loss, and stopped within 24 hours of surgery.
2. Upper GI & bariatric · 10 % peso nell’esame · 0 lessons+
- Upper GI bleeding: resuscitate, give a PPI after endoscopy, and treat high-risk stigmata (spurting vessel, visible vessel, adherent clot) endoscopically with a combination of adrenaline injection plus a second modality; rebleeding after successful endoscopic therapy is treated with repeat endoscopy before surgery or radiology.
- Bariatric surgery is indicated for BMI 35 kg/m2 or more regardless of comorbidity and may be considered from 30 kg/m2 with metabolic disease. Sleeve gastrectomy raises reflux risk; Roux-en-Y gastric bypass is preferred when significant GORD or Barrett's is present.
- Achalasia is diagnosed by high-resolution manometry (absent peristalsis with incomplete lower sphincter relaxation); pneumatic dilation, laparoscopic Heller myotomy and peroral endoscopic myotomy (POEM) are all first-line options, and the choice follows manometric subtype and fitness.
- Locally advanced resectable gastric and oesophageal adenocarcinoma is treated with perioperative chemotherapy (FLOT for gastric/GOJ) or neoadjuvant chemoradiation (CROSS for oesophageal); D2 lymphadenectomy is standard for resectable gastric cancer in experienced centres.
3. Hepatopancreatobiliary & spleen · 11 % peso nell’esame · 0 lessons+
- Acute cholangitis (Charcot triad: fever, jaundice, right upper quadrant pain; Reynolds adds shock and confusion) needs antibiotics, resuscitation and biliary drainage, urgently if severe. ERCP is the standard drainage route; percutaneous drainage is the alternative when ERCP fails.
- Acute biliary pancreatitis: early enteral feeding, goal-directed moderate fluid resuscitation with a balanced crystalloid, no prophylactic antibiotics, cholecystectomy in the same admission for mild disease; delay until collections resolve in severe disease. Infected necrosis is managed by a step-up approach (drain first, then minimally invasive necrosectomy).
- Pancreatic head cancer: resectable disease goes to surgery with adjuvant mFOLFIRINOX; borderline or locally advanced disease receives neoadjuvant therapy. Biliary drainage before surgery is used only for cholangitis, severe symptoms, delay or neoadjuvant treatment.
- Hepatocellular carcinoma in cirrhosis is staged by BCLC: very early or early disease is resected, ablated or transplanted; intermediate disease is treated with transarterial chemoembolisation; advanced disease with systemic immune-based therapy. Liver failure (Child-Pugh B or C) limits resection.
4. Colorectal & anal · 12 % peso nell’esame · 0 lessons+
- Staging of rectal cancer with MRI defines the circumferential margin and nodal risk; threatened margin or node-positive disease usually receives neoadjuvant therapy before total mesorectal excision.
- Complicated diverticulitis with abscess over 4 to 5 cm is drained percutaneously in stable patients; colonoscopy 6 to 8 weeks later excludes cancer.
- Acute severe ulcerative colitis not improving after 3 days of intravenous steroids needs rescue therapy (ciclosporin or infliximab) and surgical review; colectomy follows failure.
- Anal squamous carcinoma is cured by chemoradiotherapy; abdominoperineal excision is salvage. Chronic fissure failing medical therapy is treated with sphincterotomy or botulinum toxin.
5. Hernia & abdominal wall · 6 % peso nell’esame · 0 lessons+
- Asymptomatic inguinal hernia in men can be observed; repair is offered when symptoms appear. Femoral hernias in women carry a high risk of strangulation and need mesh repair.
- Endoscopic (TEP/TAPP) repair reduces chronic pain and speeds recovery in primary unilateral inguinal hernia; use a different plane for recurrent hernia.
- Mesh repair beats suture repair for umbilical hernias over 1 cm and incisional hernias; sublay is the preferred mesh plane.
- Optimise modifiable risks (BMI, smoking, diabetes) before elective incisional hernia repair; in contaminated fields consider tissue repair or biological mesh.
6. Breast & endocrine surgery · 8 % peso nell’esame · 0 lessons+
- Sentinel node biopsy is standard for clinically node-negative invasive breast cancer; neoadjuvant systemic therapy suits HER2-positive and triple-negative disease with large tumours or node-positive status.
- Persistent unilateral nipple eczema needs biopsy to exclude Paget disease; lactational abscess is managed by aspiration with antibiotics.
- Bethesda V and VI thyroid cytology go to surgery; total thyroidectomy with neck dissection for high-risk papillary cancer; exclude phaeochromocytoma first in MEN2.
- Symptomatic post-thyroidectomy hypocalcaemia needs IV calcium; phaeochromocytoma needs alpha-blockade before beta-blockade.
7. Vascular surgery · 8 % peso nell’esame · 0 lessons+
- Elective AAA repair at 5.5 cm or more in men; ruptured AAA gets permissive hypotension and rapid repair, EVAR if anatomy allows.
- Type A dissection needs emergency open repair; uncomplicated type B is treated medically with anti-impulse therapy.
- Claudication: exercise, risk factors, antiplatelet and statin. Chronic limb-threatening ischaemia and acute limb ischaemia need urgent revascularisation; watch for compartment syndrome after reperfusion.
- Symptomatic carotid stenosis (50-99 per cent) should be treated within 14 days; superficial venous reflux is treated with endovenous ablation; proximal DVT needs three months of anticoagulation.
8. Trauma & burns · 12 % peso nell’esame · 0 lessons+
- Primary survey (ABCDE): treat life threats as found; unstable blunt trauma with positive FAST goes to laparotomy, and tension pneumothorax is decompressed clinically.
- Haemorrhage control: balanced transfusion, early tranexamic acid, pelvic binder, damage control surgery in the lethal triad.
- Non-operative management is first line for stable blunt splenic and liver injury; hard signs of vascular or neck injury need exploration.
- Burns: Parkland formula, escharotomy for constriction, early intubation in inhalation injury, burn centre referral for face, hand or large burns.
9. Acute abdomen & emergency surgery · 9 % peso nell’esame · 0 lessons+
- Appendicitis: appendicectomy is standard; abscess is drained then interval surgery considered; older patients need colonoscopy to exclude tumour.
- Adhesive small bowel obstruction without ischaemia: nasogastric decompression, fluids and water-soluble contrast; operate for peritonitis, ischaemia or failure at 48-72 hours.
- Perforated duodenal ulcer: resuscitate, antibiotics, surgical patch; cholangitis needs urgent drainage; mild gallstone pancreatitis gets cholecystectomy the same admission.
- Time-critical emergencies: ruptured AAA, mesenteric ischaemia, testicular torsion, necrotising infection, infected obstructed kidney.
10. Surgical oncology · 6 % peso nell’esame · 0 lessons+
- Resectable gastric and oesophageal adenocarcinoma beyond early stage: perioperative or neoadjuvant therapy plus surgery (D2 gastrectomy).
- Biopsy sarcoma by planned core biopsy at a specialist centre; retroperitoneal sarcoma needs en bloc resection.
- Pancreatic cancer: borderline resectable gets neoadjuvant therapy; resected disease gets adjuvant chemotherapy; non-functioning NET over 2 cm is resected.
- RAS mutation excludes anti-EGFR therapy; dMMR/MSI-high predicts checkpoint inhibitor response; high-risk GIST gets three years of imatinib.
11. Surgical sciences, wound healing & infection · 8 % peso nell’esame · 0 lessons+
- Prophylactic antibiotics are given within 60 minutes before incision and redosed in long operations or major blood loss; do not continue for days after surgery.
- Superficial SSI is treated by opening and draining the wound; necrotising infection needs immediate radical debridement; burst abdomen is an emergency.
- Wound healing phases: haemostasis, inflammation, proliferation (collagen III, angiogenesis), remodelling (collagen I). Vitamin C is a cofactor for collagen synthesis.
- Optimise diabetes, nutrition and smoking before elective surgery; use alcohol-based chlorhexidine; clip hair rather than shave; use drains selectively.
L’esame MOH Kuwait Specialist General Surgery
Quante domande ha l’esame MOH Kuwait Specialist General Surgery?+
non pubblicato. Il numero esatto di domande, il tempo e la soglia sono confermati nella sua prenotazione.
Quali argomenti pesano di più?+
Gli argomenti principali sono Colorectal & anal (12 %), Trauma & burns (12 %), Hepatopancreatobiliary & spleen (11 %). Il corso copre 11 argomenti con 0 capitoli in totale.
Come mi preparo all’esame MOH Kuwait Specialist General Surgery?+
Studi i capitoli argomento per argomento, ripassi gli appunti chiave e si eserciti con simulazioni a tempo nel formato della sua autorità.
Domande
Per quanto tempo ho accesso?+
L’accesso dura 90 giorni dal pagamento per il paese e la professione scelti.
Quali dispositivi posso usare?+
Qualsiasi browser su computer, tablet o telefono, più l’app MediFlow con lo stesso account.
Posso avere un rimborso?+
Legga la nostra politica di rimborso prima dell’acquisto. Politica di rimborso

iPhone · iPad
MediFlow Exam Prep
Si prepari sul Suo iPhone per DHA, DOH, MOHAP, SCFHS e altri esami di abilitazione del Golfo.

L’esame è il suo unico passo aperto?
Verifichi prima se l’esame le serve davvero e quale titolo può aspettarsi. Un consulente la richiama e risponde alle sue domande.
Verifica dei requisiti- 1Chiamata su WhatsApp all’orario che sceglie
- 2Verifica dei requisiti secondo le norme ufficiali
- 3Il suo piano con prezzi fissi e passi chiari