
🇸🇦 SCFHS
Specialist Obstetrics & Gynecology Saudi Arabia
Physicians preparing for the Obstetrics and Gynecology exams of DHA, DOH, MOHAP, Qatar DHP and SCFHS
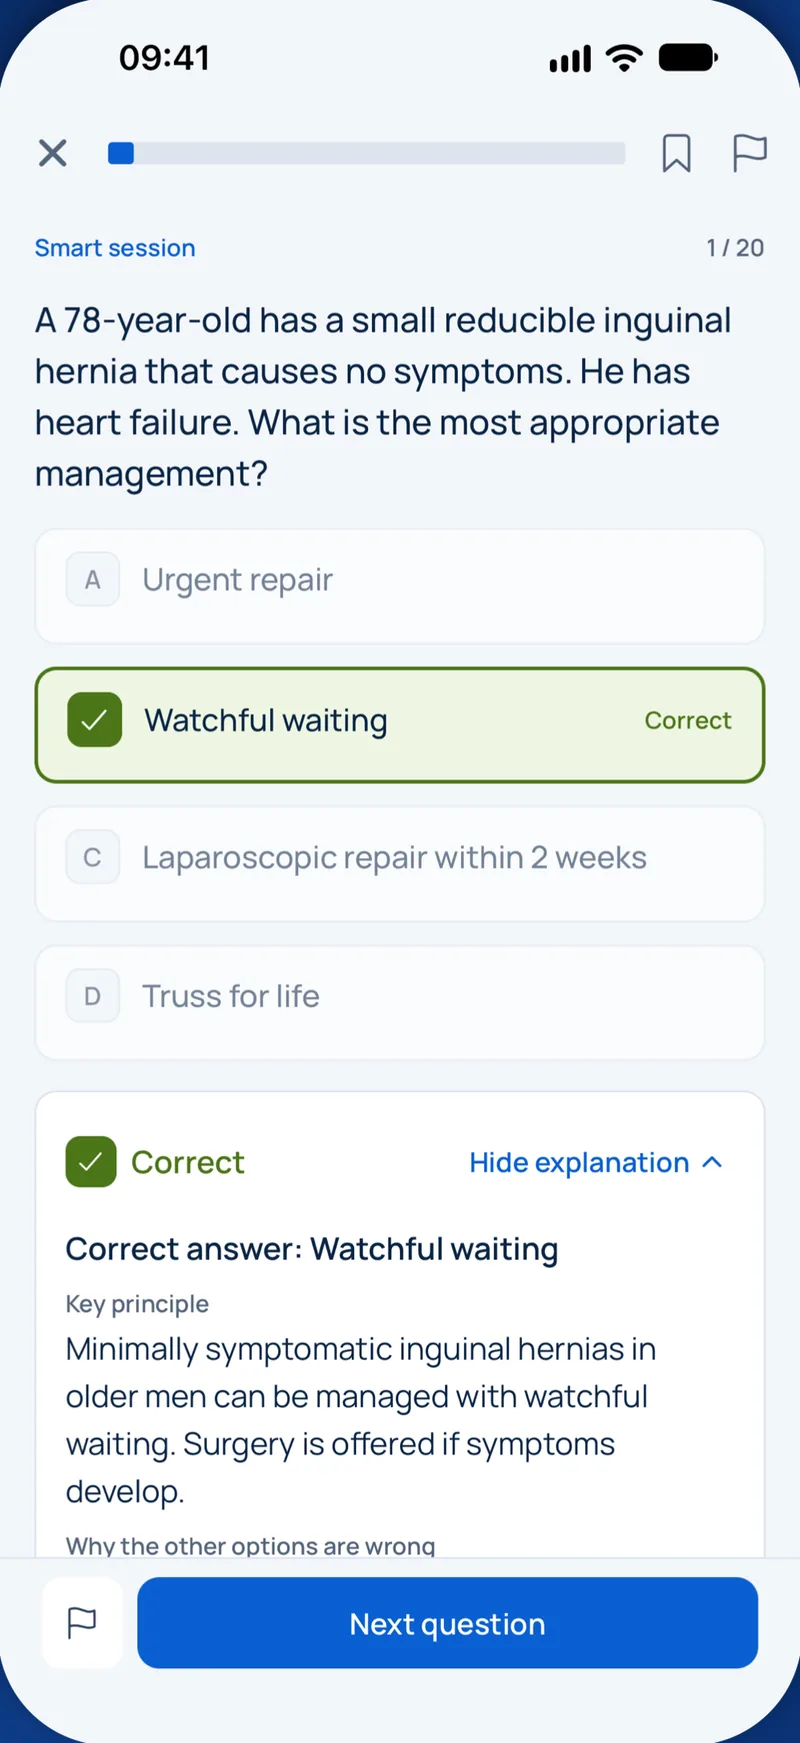
Voorbeeldvraag
Which antenatal screening test is offered to all pregnant women at the booking visit to prevent neonatal infection?
Keys: 1–5 or A–E to choose, Enter to check and continue, F to mark.
Original MediFlow content, not official exam questions. Medical review in progress.
Syllabus and high-yield notes
1. Antenatal care & prenatal screening · 14 % gewicht in het examen · 0 lessons+
- Low-dose aspirin 75-150 mg from 12 weeks is offered for one high-risk or two moderate risk factors for pre-eclampsia.
- Rh(D) negative women receive anti-D prophylaxis at 28 weeks and after delivery of an Rh positive baby; MCA PSV above 1.5 MoM suggests fetal anaemia.
- Cell-free DNA is a high-sensitivity screening test but a positive result still needs CVS or amniocentesis confirmation.
- IADPSG/WHO gestational diabetes thresholds (75 g OGTT): fasting 5.1, 1 hour 10.0, 2 hours 8.5 mmol/L; one abnormal value suffices.
2. Labour & delivery · 12 % gewicht in het examen · 0 lessons+
- Failure of cervical change in the active phase is managed with oxytocin augmentation if contractions are inadequate; caesarean follows arrest despite adequate contractions.
- Shoulder dystocia: McRoberts with suprapubic pressure first, then internal manoeuvres and posterior arm; avoid fundal pressure and strong traction.
- Uterine rupture risk in trial of labour after caesarean is raised by prostaglandins; oxytocin is used with caution.
- Postpartum haemorrhage: four Ts; oxytocin, tranexamic acid, then carboprost or ergometrine as contraindications allow.
3. Obstetric complications · 14 % gewicht in het examen · 0 lessons+
- Severe-range hypertension (160/110 mmHg or above) is treated within 30-60 minutes; magnesium sulphate prevents eclampsia and calcium gluconate reverses toxicity.
- Placenta praevia with bleeding: no digital examination; steroids, blood and planned caesarean. Praevia over a scar raises accreta risk.
- Cholestasis of pregnancy: bile acids drive stillbirth risk; ursodeoxycholic acid for symptoms and timing delivery by level.
- Obstetric DIC consumes fibrinogen first, replace with cryoprecipitate or fibrinogen concentrate.
4. Postpartum & breastfeeding · 6 % gewicht in het examen · 0 lessons+
- Uterine atony causes about 70% of postpartum haemorrhage; massage, uterotonics, tranexamic acid and escalation follow a stepwise protocol.
- Give tranexamic acid 1 g IV within 3 hours of birth for any PPH, repeating once after 30 minutes if bleeding continues.
- Endometritis is polymicrobial; clindamycin plus gentamicin is a standard regimen.
- Postpartum blues peak at days 3 to 5; psychosis is an emergency requiring admission.
5. General gynecology · 12 % gewicht in het examen · 0 lessons+
- Methotrexate for ectopic needs stability, unruptured mass, hCG below about 5,000 IU/L and no fetal cardiac activity.
- Heavy menstrual bleeding without structural cause: LNG-IUS first, tranexamic acid or NSAIDs as alternatives.
- Postmenopausal bleeding with endometrial thickness above 4 mm needs tissue sampling.
- PID is treated empirically with ceftriaxone, doxycycline and metronidazole, and partners are treated.
6. Reproductive endocrinology & infertility · 10 % gewicht in het examen · 0 lessons+
- Letrozole is first-line for ovulation induction in PCOS; clomifene is second-line.
- Agonist trigger with antagonist protocol and freeze-all minimises OHSS.
- Women aged 35 or more are referred after 6 months of trying; reserve markers include AMH and antral count.
- Hydrosalpinx should be removed or occluded before IVF.
7. Urogynecology & pelvic floor · 6 % gewicht in het examen · 0 lessons+
- Stress incontinence: supervised pelvic floor training for at least 3 months first; midurethral sling is the standard operation.
- Overactive bladder: bladder training, then antimuscarinic or beta-3 agonist; botulinum toxin and neuromodulation are third-line.
- Treat prolapse only if symptomatic; pessary is a valid first choice.
- Continuous leakage after surgery or obstructed labour suggests fistula.
8. Gynecologic oncology · 8 % gewicht in het examen · 0 lessons+
- Early endometrial cancer: hysterectomy with BSO and sentinel node assessment; adjuvant therapy is guided by molecular class (POLE, MMRd, p53abn, NSMP).
- Locally advanced cervical cancer (IB3 to IVA) is treated with cisplatin chemoradiation and brachytherapy.
- BRCA1 carriers: risk-reducing BSO at 35 to 40 years after childbearing; PARP inhibitor maintenance after platinum response.
- hCG plateau or rise after a mole defines GTN; low-risk disease is cured with single-agent chemotherapy.
9. Contraception & sexual health · 6 % gewicht in het examen · 0 lessons+
- Combined hormonal contraception is contraindicated (UKMEC 4) in migraine with aura, prior VTE, smoking aged 35 or more with heavy use, and before 6 weeks postpartum if breastfeeding.
- Copper IUD is the most effective emergency contraception, within 5 days.
- Enzyme inducers such as rifampicin reduce efficacy of pills and implants; use an IUD.
- Doxycycline 7 days is first-line for chlamydia.
10. Fetal medicine & imaging · 6 % gewicht in het examen · 0 lessons+
- Nuchal translucency of 3.5 mm or above warrants diagnostic testing and a detailed scan whatever the calculated risk.
- cfDNA is a screening test; a high-risk result is confirmed by CVS or amniocentesis.
- FGR is managed by Doppler: absent end-diastolic flow prompts delivery planning by 32 to 34 weeks with steroids and magnesium.
- MCA PSV above 1.5 MoM suggests significant fetal anaemia.
11. Ethics, safety & law · 6 % gewicht in het examen · 0 lessons+
- A capacitous pregnant woman may refuse any treatment, including caesarean section; her husband cannot consent for her.
- Competent adolescents can receive confidential contraceptive care; assess for exploitation and safeguarding concerns.
- Duty of candour requires honest disclosure, apology and incident reporting after adverse events.
- In emergencies without capacity, life-saving treatment proceeds in the best interests of the patient with documentation.
Over het SCFHS Specialist Obstetrics & Gynecology-examen
Hoeveel vragen heeft het SCFHS Specialist Obstetrics & Gynecology-examen?+
niet gepubliceerd. Het exacte aantal vragen, de tijd en de slaaggrens staan in uw boeking.
Welke onderwerpen wegen het zwaarst?+
De grootste onderwerpen zijn Antenatal care & prenatal screening (14 %), Obstetric complications (14 %), Labour & delivery (12 %). De cursus omvat 11 onderwerpen met in totaal 0 hoofdstukken.
Hoe bereid ik me voor op het SCFHS Specialist Obstetrics & Gynecology-examen?+
Werk de hoofdstukken onderwerp voor onderwerp door, herhaal de kernnotities en oefen daarna met getimede proefexamens in het formaat van uw instantie.
Vragen
Hoe lang heb ik toegang?+
De toegang loopt 90 dagen vanaf betaling voor het gekozen land en beroep.
Welke apparaten kan ik gebruiken?+
Elke browser op computer, tablet of telefoon, plus de MediFlow-app met hetzelfde account.
Kan ik mijn geld terugkrijgen?+
Lees vóór aankoop ons terugbetalingsbeleid. Terugbetalingsbeleid

iPhone · iPad
MediFlow Exam Prep
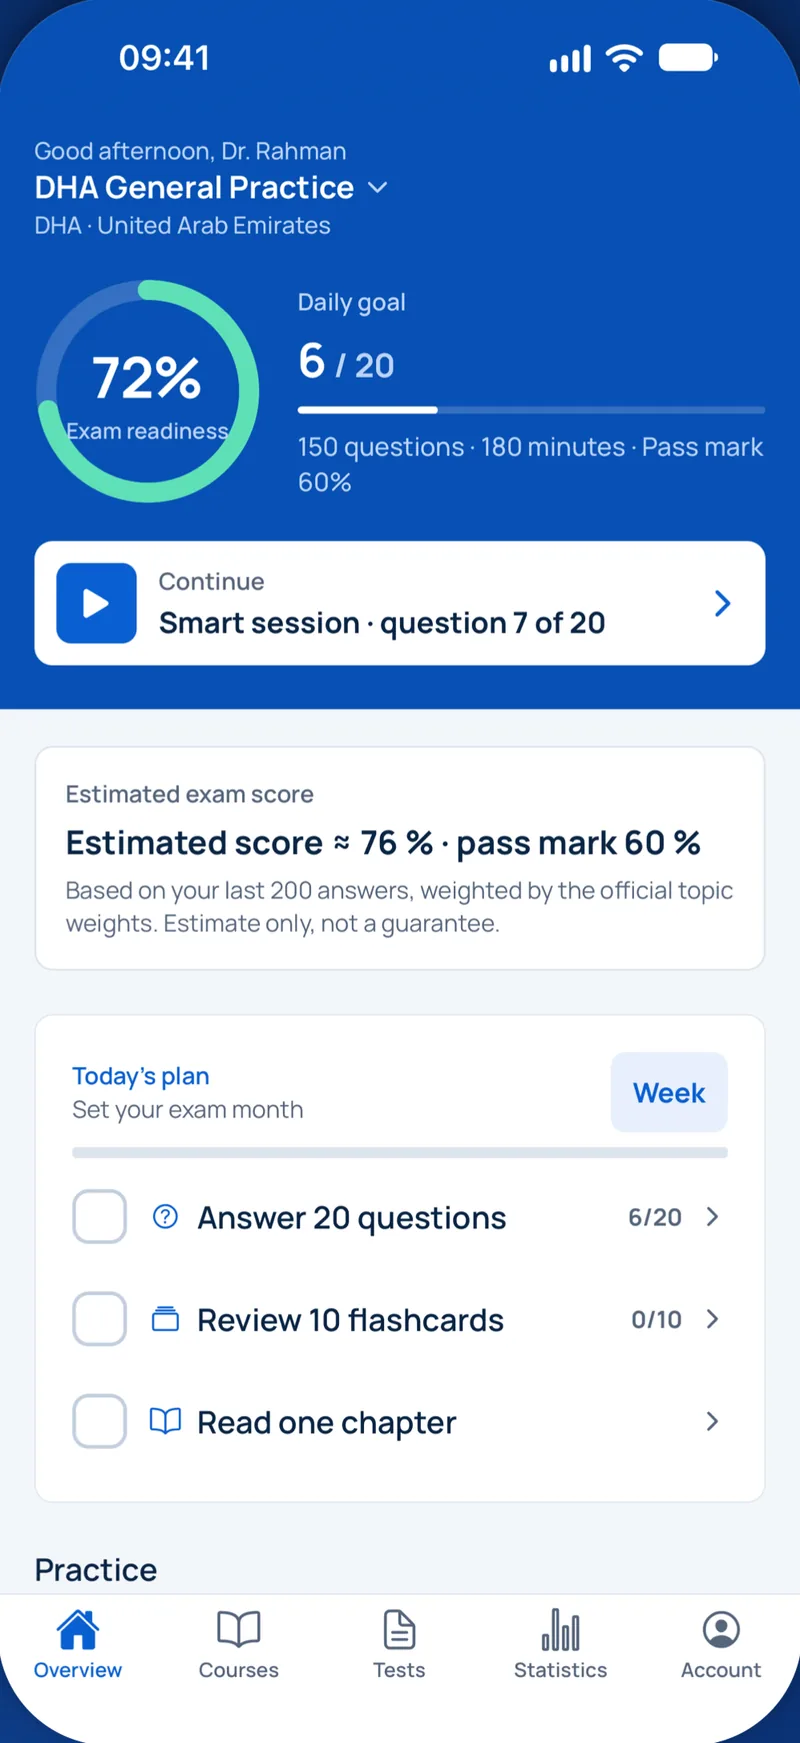
Bereid u op uw iPhone voor op DHA, DOH, MOHAP, SCFHS en andere licentie-examens in de Golf.

Is het examen uw enige open stap?
Controleer eerst of u het examen echt nodig hebt en welke titel u kunt verwachten. Een adviseur belt u terug en beantwoordt uw vragen.
Geschiktheidscheck- 1Terugbellen via WhatsApp op een tijd die u kiest
- 2Geschiktheidscheck volgens de officiële eisen
- 3Uw plan met vaste prijzen en duidelijke stappen